September 24, 2026
6 min
An AI receptionist checks real-time schedules, matches providers and rooms, and confirms before updating, helping dental practices reschedule appointments without double-booking.
December 1, 2025
8 min
Explore how Google Ads, Facebook Ads, and Local SEO compare on ROI, metrics, and effectiveness for businesses. Learn where to invest for the best returns.

Every practice owner eventually asks the same question: where does the next marketing dollar actually work hardest, Google Ads, Facebook Ads, or Local SEO? The honest answer is that ROI by channel depends less on which platform you pick and more on how you measure it. Google Ads gives you the fastest read on demand, often producing a booked patient within days if your keywords and landing pages are dialed in. Facebook and Meta Ads trade speed for reach, they're where creative testing and retargeting build a pipeline that platform reporting alone tends to flatter. Local SEO for dentists is the slow build, nearly invisible for the first few months, then quietly compounding into the channel that brings in patients without a bid war attached to every click.
If you're trying to decide where your budget goes this quarter, the short version is this: Google Ads wins when you need patients now and can defend your cost per acquisition. Meta wins when your funnel rewards experimentation and you're patient enough to refresh creative on a schedule. Local SEO wins over a 3 to 12 month horizon for any multi-location group that wants a channel competitors can't simply outbid. None of that matters much, though, if your ad platforms and your practice management system aren't talking to each other. A dashboard like ConvertLens exists precisely because marketing reporting without PMS data is a guessing game dressed up as analytics.
Before comparing platforms, it helps to agree on what "ROI" is actually measuring. Most practices default to whatever number their ad platform surfaces, which is a mistake, since platform dashboards tend to grade their own homework. Here's what to track instead, and why each metric tells a different part of the story.
Cost per acquisition (CPA), sometimes called cost per lead, is the real price tag on a new patient or booked appointment. Watch it over a 0 to 30 day window for a quick read, and 30 to 90 days for slower channels. Last click attribution is the default almost everyone starts with, but it's shallow. As your data volume grows, move toward data driven or multi touch attribution, since last click tends to over credit whichever channel happens to close the deal. The biggest trap here is sloppy UTM tagging: a lead that gets lost between a phone call and a booked appointment doesn't disappear from your revenue, it just disappears from your reporting.
ROAS, or return on ad spend, tells you how many dollars come back for every dollar you put into a specific campaign. It's the right metric for transactional, short cycle funnels. The catch is that platform reported ROAS often inflates itself, counting assisted conversions as if they were the whole story. Cross check it against a full funnel view before you trust it enough to shift budget.
LTV to CAC ratio answers the bigger question: is this patient relationship actually compounding, or are you running in place? For dental and orthodontic practices with recurring visits, this needs 6 to 12 months of data and, ideally, a CRM or PMS feed rather than a guess based on platform reported leads alone. A widely cited healthy target is 3 to 1 (lifetime value three times acquisition cost); dip under 2 to 1 and something in your funnel or your channel mix needs attention.
Conversion rate is the simplest gut check on how many visitors actually become leads or booked patients, and it deserves a rolling 0 to 30 day review since GA4's event based tracking drifts if nobody's watching for misfired goals.
Time to conversion rounds things out, showing how long a lead takes to become a patient once they enter your funnel. Position based or decay attribution models handle this better than last click, because they don't pretend every touchpoint mattered equally.
Last click attribution is the easiest model to set up, and it's also the most biased one, it hands almost all the credit to whichever channel touched the patient last, which in practice usually means search. As soon as you have enough volume to justify it, move to data driven or multi touch attribution, which spreads credit across the actual patient journey rather than crowning a winner by default. For bigger, boardroom level budget decisions, marketing mix modeling (MMM) looks at the whole system rather than isolated campaigns. And when you genuinely can't tell if a channel is driving incremental patients or just taking credit for people who would have booked anyway, run a holdout test: pull a geography or audience segment out of that channel for three to four weeks and watch what actually changes.
Getting this right depends on clean measurement. Standardize your UTM naming, lean on server side tracking (Meta's Conversions API, server side GTM) to recover data lost to browser privacy changes, and, above all, pipe your CRM or PMS data back into whatever dashboard you're using to judge performance. If your platform reported CPA and your actual booked revenue tell two different stories, the problem isn't the channel, it's the plumbing. That's the exact gap tools like ConvertLens's dental ROI tracking are built to close, connecting ad spend to production revenue instead of leaving you to reconcile spreadsheets by hand.
Here's how the three channels stack up on the numbers that actually matter, pulled from current industry benchmarks and 2026 dental marketing data.
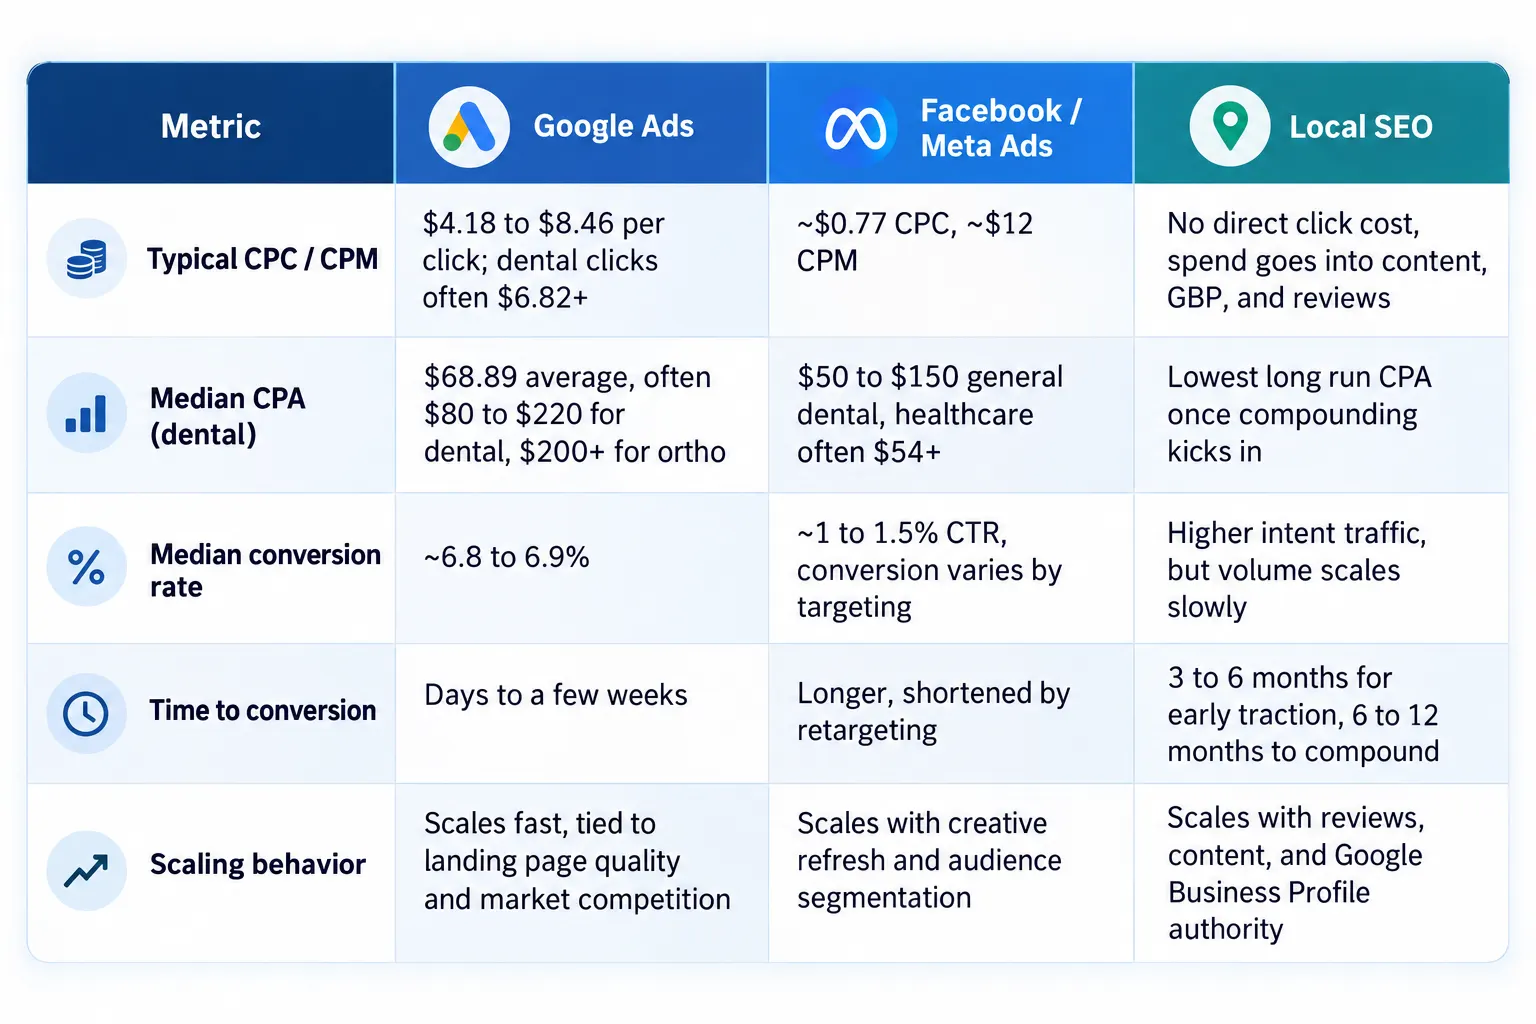
A word on those numbers: a 2026 UK dental marketing analysis found Google Search CPLs running £45 to £120, with Meta CPLs at roughly £8 to £35, and cost per booked patient landing between £120 and £450 depending on treatment value. The pattern holds across markets, Google costs more per click but converts higher intent traffic fast; Meta costs less per click but needs more nurturing before it turns into a booked chair.
Google Ads is the channel for catching people who are already looking. It rewards teams that are disciplined about pruning underperforming keywords and ruthless about passing real booked appointments back from the PMS or CRM into the ad platform, otherwise you're optimizing toward a number that was never true. Expect search CPCs in the $4 to $9 range generally, dental specific clicks pushing past $6.80, and a conversion rate hovering around 6.8%.
Facebook and Meta Ads function more like a discovery engine than a search engine. Clicks are cheap, roughly $0.77 on average, but the funnel demands creative that gets refreshed regularly and server side tracking that survives iOS privacy changes. Healthcare specific ROAS tends to sit lower than ecommerce benchmarks, around 1.2 to 2.2x, with dental CPAs often running $50 to $150. The practices that win here treat Meta as a testing ground for messaging, then feed booked outcomes back into the CRM so the next campaign gets smarter instead of guessing again.
Local SEO for dentists is the hardest channel to fake and the slowest to show results, which is exactly why it compounds. There's no bid war, just Google Business Profile optimization, review velocity, and content that answers what actual patients are searching. Expect your first real traction around 3 to 6 months, with the flywheel spinning faster from month 6 onward. For multi location groups, this is often the channel with the best patient acquisition cost over a full year, especially once your reviews and citations are tied back to actual booked outcomes rather than tracked in isolation. If your practice serves several locations, our guide on local dental lead generation walks through the build order that tends to work.
Most ROI comparisons stop at the channel level and skip the part that actually determines outcomes: how much you should be spending on each channel given where your practice is right now.
A new practice with limited brand recognition typically leans harder on paid search, something like 50 to 60% of budget in Google Ads for immediate demand capture, 20 to 30% in Meta for awareness and retargeting, and the rest seeded into Local SEO fundamentals even though the payoff is months away. A growing practice with an established patient base can start shifting weight, often closer to 35% Google, 30 to 40% Meta as creative testing matures, and 25 to 30% into SEO as organic traffic starts contributing meaningfully to the blended CPA. An established, multi location practice usually sees the best long run economics by leaning into Local SEO, sometimes 35% or more of budget, since blended CPA keeps dropping as organic contribution grows, while Google and Meta shrink to roughly a quarter each, reserved for demand spikes and specific service pushes.
The mistake we see constantly: practices treat this as a one time decision instead of a quarterly recalibration. Track revenue per lead against cost per lead every month, and if you're managing more than one location, our breakdown on how multi location dental groups calculate ROI covers the blended attribution math in more depth than we can here.
None of the comparisons above mean anything if your measurement is broken. A few non negotiables:
Lock down UTM naming conventions (lowercase, dashes replaced with consistent separators, versioned templates) and check them weekly, not quarterly, since a poisoned data set is hard to un-poison. Define real business events in GA4, lead submitted, phone call, appointment booked, rather than settling for pageviews. Layer in server side tracking through GTM server side or Meta's Conversions API so privacy blockers stop eating your conversion data. And connect your CRM or PMS so leads, appointments, and revenue reconcile against what the ad platforms report, not just once, but as a standing weekly habit.
This is where most practices quietly lose the thread, because why dental marketing ROI falls without proper attribution usually comes down to exactly this: nobody closed the loop between what an ad platform claims and what actually got booked. Our guide to attribution models for dental marketing goes deeper on choosing between last click, multi touch, and MMM if you're ready to move past guesswork. And if Google Ads specifically is the channel you're trying to prove out, connecting Google Ads to dental production revenue is the piece most practices skip.
There isn't a single right answer to which channel wins, only a better question: what are you optimizing for, how long can you wait for the return, and how well does your measurement reflect what actually happened versus what a platform dashboard claims happened? Short cycles favor Google Ads. Longer horizons reward the patience Meta and Local SEO both require in different ways. For any practice managing more than one location, the real unlock isn't picking a winner, it's centralizing measurement so every channel gets judged against the same yardstick.
If you're ready to see your own blended CPA, ROAS, and LTV to CAC numbers in one place instead of stitched together from three different dashboards, ConvertLens's marketing ROI tracking and dental KPI dashboard were built to answer exactly this question, with your own PMS data behind every number.
Which channel delivers the fastest ROI?
Google Ads, typically. For high intent searches, a well built campaign can produce a booked appointment within days to a few weeks, provided your landing page and offer actually match what people are searching for.
Can Facebook or Meta Ads ever outperform Google on ROI?
Yes, particularly in creative driven or impulse adjacent funnels where retargeting is disciplined and creative gets refreshed often. Reported ROAS for Meta campaigns can approach 3x in the right vertical, though healthcare specific benchmarks tend to run lower than ecommerce averages.
How long does Local SEO take to pay back for a dental practice?
Most practices see early signals at 3 to 6 months, with meaningful compounding and a falling cost per acquisition from 6 months onward. Twelve months is a realistic point to judge the channel fairly.
What's a healthy LTV to CAC ratio for a dental practice?
A 3 to 1 ratio is commonly cited as healthy. Below 2 to 1 usually signals a funnel or channel mix problem worth investigating; above 5 to 1 can mean you're actually underspending relative to your growth potential.
How should a practice with a $1,000 to $5,000 monthly budget split it?
Google Ads typically leads for immediate demand capture, Meta plays a supporting role for testing and retargeting around 20 to 30% of spend, and Local SEO should start now regardless of budget size, since it's the one channel where waiting costs you compounding time you can't buy back later.
What's the minimum tracking setup to trust these numbers?
GA4 with clean event definitions, disciplined UTM tagging, conversion tracking on both Google and Meta (Pixel plus Conversions API), and a CRM or PMS integration that reconciles leads against actual booked revenue.



September 24, 2026
6 min
An AI receptionist checks real-time schedules, matches providers and rooms, and confirms before updating, helping dental practices reschedule appointments without double-booking.

September 23, 2026
6 min
AI receptionists can explain insurance verification, collect plan details, clarify billing terms, and answer payment questions, then pass complex account issues to your billing team.

September 21, 2026
9 min
Improve dental patient experiences with engagement technology that streamlines scheduling, strengthens retention, and eases front-desk workload.
Sign Up Now & Someone from Our Team Will Be in Touch Shortly!
Use the form below to send us a message, and we’ll get back to you as soon as we can.

Track every marketing dollar and optimize patient conversions with ConvertLens. Gain valuable insights from your campaigns, ensuring you never miss a potential patient. Maximize ROI and grow your practice effortlessly.
